
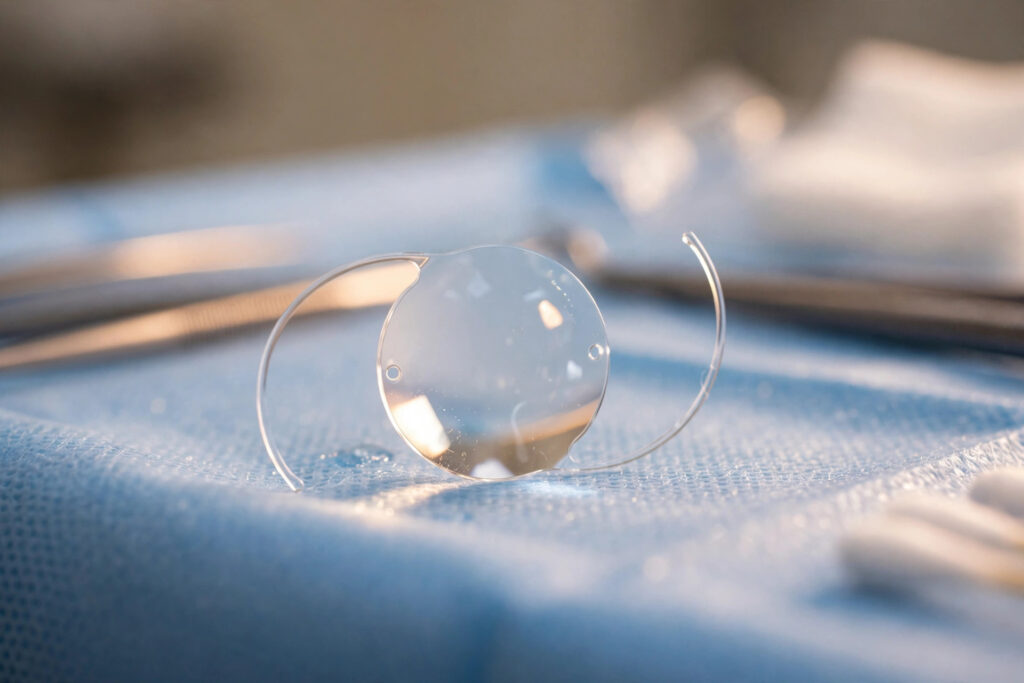
Refractive lens exchange, usually shortened to RLE, is a vision correction procedure that replaces the eye’s natural lens with an artificial intraocular lens, much like cataract surgery, but performed to correct a prescription rather than to remove a cloudy lens. It is the same operation, the same technology, and the same lens implants as modern cataract surgery; the difference is entirely in the reason for doing it. For adults typically over 45 with high prescriptions, early lens changes, or presbyopia, RLE can correct distance, intermediate, and near vision in a way no corneal laser procedure can match.
This complete guide explains how refractive lens exchange works, who it suits best, the premium lens options available in 2026, the real risks, what recovery involves, and what it costs. As with any intraocular surgery, the decision belongs in a thorough consultation: this article gives you the background to have that conversation well, not to replace it. Discuss every option with a qualified refractive eye surgeon before deciding.
Table of Contents
- What RLE Is and How It Differs from Cataract Surgery
- How the RLE Procedure Works
- Who RLE Suits Best
- Premium Lens Options in 2026
- Risks and Complications
- Recovery After RLE
- RLE Cost and Final Considerations
What RLE Is and How It Differs from Cataract Surgery
Refractive lens exchange and cataract surgery are technically the same procedure: the cloudy or clear natural lens is removed through a tiny incision and replaced with a foldable artificial intraocular lens. In cataract surgery the lens has become cloudy and vision is impaired; in RLE the lens is still clear but the patient wants freedom from glasses or contacts, often because their prescription is too high for LASIK or because presbyopia has made near vision a daily struggle. The surgical skill, the equipment, and the implants overlap almost completely.
One meaningful difference is timing and expectation. Cataract surgery is medically necessary and typically covered by insurance; RLE is elective and paid out of pocket. Because RLE patients are usually younger and have higher visual demands, lens selection tends to emphasize premium optics, multifocal or extended-depth-of-focus designs, that reduce dependence on glasses at multiple distances. The American Academy of Ophthalmology’s treatment overviews describe how these intraocular lens technologies are used across both procedures.
A practical consequence of RLE is worth understanding early: once the natural lens is replaced, you will never develop a cataract in that eye, because the structure that clouds with age is gone. For patients in their late 50s or 60s considering vision correction, this makes RLE a two-problems-one-solution proposition, addressing both the current prescription and the future cataract.
How the RLE Procedure Works
RLE is performed as outpatient surgery, one eye at a time, usually a week or two apart. After numbing drops and mild sedation, the surgeon creates a tiny incision in the cornea, opens the thin capsule holding the natural lens, and breaks the lens apart with ultrasound energy, a technique called phacoemulsification, before gently removing the fragments. The artificial lens is then folded, inserted through the same small incision, and unfolded into position inside the capsular bag. No stitches are typically needed.
Each eye takes roughly 15 to 20 minutes, and patients go home the same day with a protective shield. In 2026 many surgeons use femtosecond laser assistance for some steps, such as creating the incision and opening the lens capsule with extra precision, though skilled manual technique achieves excellent results as well. The choice between laser-assisted and traditional phacoemulsification is worth discussing, but surgeon experience matters far more than the specific platform.
Because the procedure enters the inside of the eye, the pre-operative workup is thorough: precise measurements of the eye’s length and corneal curvature determine the implant power, and the retina is examined for any weakness that the procedure could aggravate. This measurement step, called biometry, is the foundation of an accurate result, and premium practices invest heavily in getting it right.
Who RLE Suits Best
The classic RLE candidate is an adult over 45, often over 50, with a significant prescription, presbyopia, or early lens changes that make laser correction a poor fit. Very high nearsightedness or farsightedness beyond the safe range of LASIK, thin corneas, and patients already noticing that their glasses prescription keeps changing due to early cataract formation are all common profiles. For these patients, RLE addresses the actual source of the problem, the aging lens, rather than compensating for it on the cornea.
RLE is generally not for younger patients. Removing a healthy, still-accommodating natural lens in a 30-year-old sacrifices the eye’s remaining focusing ability and is rarely justified when corneal or implantable-lens options exist. Patients with certain retinal conditions, uncontrolled glaucoma, or corneal diseases may also be poor candidates, since intraocular surgery carries different risks than surface laser work. A comprehensive How to Read Eye Prescription Numbers“>eye exam with dilated retinal evaluation is the essential first filter.
Expectations matter as much as anatomy. RLE with premium lenses dramatically reduces glasses dependence, but no lens restores the natural focusing of youth perfectly, and some patients still prefer thin glasses for prolonged reading or night driving. Candidates who understand these trade-offs report the highest satisfaction.
Premium Lens Options in 2026
The lens choice defines the RLE result, and options in 2026 are more sophisticated than ever. Monofocal lenses provide crisp vision at one distance, usually set for distance, with reading glasses needed for near work; they offer the sharpest optical quality and the lowest cost. Multifocal lenses split light between distance and near focal points, giving strong glasses independence but sometimes causing halos around lights at night. Extended depth of focus, or EDOF, lenses stretch a single focal range to cover distance and intermediate vision smoothly, with fewer nighttime visual effects than multifocals but weaker very-near vision.
Toric versions of each design correct astigmatism, and for many patients a toric lens is the difference between a good and an excellent result. Light-adjustable lenses, which allow fine-tuning of the prescription with UV light treatments after surgery, represent the newest frontier and appeal to patients wanting maximum precision. Your surgeon matches the lens to your prescription, eye anatomy, lifestyle, and tolerance for visual trade-offs.
This is also where honest counseling earns its keep. A golfer, a night-shift driver, and an avid reader have genuinely different optical priorities, and the “best” lens varies accordingly. Advances in CR-39 vs Polycarbonate Lenses“>lens technology keep expanding the menu, but the consultation, not the brochure, should drive the choice.
Risks and Complications
RLE carries the risks of intraocular surgery, which are different in kind from LASIK’s risks. Infection inside the eye, though rare with modern sterile technique and antibiotic protocols, is the most serious concern and the reason post-operative drops and hygiene instructions must be followed exactly. Retinal detachment is a known risk after lens surgery, slightly elevated in highly nearsighted eyes, which is why the pre-operative retinal examination and prompt reporting of flashes or new floaters matter so much.
More common but less serious issues include prolonged inflammation, temporary pressure spikes, and swelling at the center of the retina that usually responds to treatment. A frequent later occurrence is clouding of the membrane behind the implant, called posterior capsule opacification, which is easily treated with a quick in-office laser procedure. None of these are reasons to avoid RLE when it is indicated, but all of them are reasons to choose an experienced surgeon and to keep every follow-up appointment.
Visual side effects depend on the lens type: multifocal designs trade some contrast and add halos for near vision, while monofocals keep optics clean at the price of reading glasses. Understanding which trade-offs you are accepting, in your own words, before surgery day is the mark of a good consent process. The FDA’s overview of vision correction procedures provides neutral background on how lens-based options compare with laser ones.
Recovery After RLE
RLE recovery is generally quick and comfortable. Vision is often functional the next day, though it may fluctuate for a week or two as the eye settles and any residual inflammation resolves. Prescribed antibiotic and anti-inflammatory drops are used on a tapering schedule, and a protective shield is worn while sleeping for the first several nights. Most patients return to desk work within a few days.
Restrictions resemble those after cataract surgery: no eye rubbing, no swimming or hot tubs until cleared, and careful hygiene around the eyes. Heavy lifting and strenuous exercise wait for the surgeon’s approval, usually within a couple of weeks. Because the eyes are done one at a time, the period between surgeries involves temporary imbalance, with one corrected eye and one still in its old prescription; most patients adapt quickly, and some wear a contact lens in the unoperated eye to bridge the gap.
Full visual stabilization, including adaptation to a multifocal or EDOF lens’s optical design, can take several weeks to a few months. The brain needs time to learn to use the new optics, and patience during this neuroadaptation period pays off. Follow-up visits confirm the lens position, eye pressure, and retinal health at each stage.
RLE Cost and Final Considerations
RLE is among the more expensive vision correction options, reflecting the operating suite, the premium implant, and the surgeon’s intraocular expertise. Many clinics quote in the range of several thousand dollars per eye, with premium multifocal or toric lenses adding to the total. Because it is elective, insurance does not cover RLE the way it covers cataract surgery, though financing plans and health savings accounts are commonly used.
When weighing RLE against alternatives, consider the full picture. For a 58-year-old with a high prescription and early lens changes, RLE may cost more upfront than LASIK but permanently solves both the prescription and the coming cataract, while premium Reading Glasses vs Prescription Readers: What’s the Difference?“>eyeglasses or contact lenses remain the no-surgery path. There is no universally right answer, only the right answer for a particular eye and life.
The final consideration is the surgeon. RLE demands the judgment to choose the right lens, the skill to place it perfectly, and the honesty to recommend against surgery when expectations cannot be met. Seek a board-certified ophthalmologist with deep experience in premium lens surgery, get a written quote with the lens model named, and take time with the decision. Your eyes deserve nothing less than an unhurried, fully informed choice.